autoscriber analytics insights data visualization stands at the bleeding edge of a quiet revolution transforming modern healthcare ecosystems. Where spoken words once vanished into the sterile air of examination rooms, advanced architectures now capture every phonetic nuance, transmuting raw conversational soundwaves into structured intelligence dashboards. This meticulous orchestration of acoustic telemetry bridges the chasm between fleeting human interaction and enduring operational mastery, empowering medical institutions to perceive their daily rhythms with astonishing clarity.
Beneath the surface of routine clinical encounters lies a vast, untapped ocean of behavioral data. As automated engines decode linguistic patterns, emotional trajectories, and workflow efficiencies, healthcare leaders gain unprecedented visibility into systemic bottlenecks and patient sentiments. By converting amorphous dialogues into vibrant, responsive visual metrics, organizations can navigate complex operational landscapes with profound precision, ensuring that technology serves not merely to record, but to elevate the entire continuum of patient care.
Modern medical transcription platforms now transform raw audio recordings into structured intelligence dashboards.

Source: devtodev.com
Transforming raw numbers into vibrant visual stories reveals hidden operational truths. Today, organizations harness konsolidator data visualization features to paint a crystal-clear picture of fiscal health. Ultimately, mastering these dynamic dashboards empowers leaders to steer every future venture with absolute confidence and strategic clarity.
The evolution of clinical documentation has transcended traditional text generation, emerging as a sophisticated discipline where ambient soundscapes are meticulously distilled into actionable clinical intelligence. Healthcare environments no longer view patient encounters as fleeting spoken moments, but rather as rich reservoirs of quantifiable operational and diagnostic data. This paradigm shift empowers medical institutions to decode the hidden rhythms of clinical workflows, bridging the gap between spoken dialogue and evidence-based visualization systems.
State-of-the-art telemetry engines operate continuously within the background of modern examinations, capturing every cadence, hesitation, and clinical descriptor uttered during patient-provider interactions. By converting ephemeral acoustic waves into rigid mathematical constructs, these systems illuminate patterns that previously remained obscured within unstructured text files. Healthcare administrators and clinicians now interact with dynamic visualization dashboards that translate complex verbal exchanges into immediate, intuitive visual metrics.
Architecture of automated transcription telemetry engines
Beneath the surface of contemporary medical recording interfaces lies a robust multi-layered telemetry architecture designed to ingest, process, and broadcast acoustic data streams in real time. This intricate framework ensures that high-fidelity audio captured during patient consultations undergoes rigorous filtering, noise reduction, and semantic segmentation before reaching analytical endpoints. The underlying infrastructure relies on distributed cloud nodes capable of handling concurrent streams from thousands of clinical rooms without latency degradation.
Telemetry data collection begins at the point of capture through specialized spatial microphones that isolate physician and patient voices from background hospital ambient noise. These raw audio streams are immediately tagged with metadata timestamps, department identifiers, and session tokens, creating a traceable digital lineage for every spoken syllable. The primary components driving this data extraction framework include:
- Edge-computing audio capture modules that compress losslessly while preserving critical frequency ranges necessary for phonetic analysis.
- Acoustic streaming brokers that queue and distribute encrypted audio packets to downstream neural processing clusters.
- Distributed telemetry daemons that monitor system health, transcription confidence scores, and real-time processing throughput across enterprise nodes.
Transformation pipelines converting unstructured phonetic waveforms into quantifiable metrics
The journey from a transient acoustic wave to an immutable data point requires a sophisticated sequence of computational transformation stages. Initially, raw analog-to-digital conversions establish a continuous frequency spectrum, which deep neural networks then parse into discrete phonemes and morphemes using context-aware language models trained specifically on biomedical taxonomies. This deep comprehension layer resolves medical homophones and complex pharmacological terminology with unprecedented accuracy.
Once the phonetic structure is reliably converted into text strings, natural language processing engines execute entity recognition algorithms to isolate symptoms, dosages, anatomical locations, and temporal markers. These extracted elements are subsequently mapped to standardized ontological frameworks such as SNOMED-CT and ICD-10, thereby standardizing heterogeneous human speech into uniform, queryable data schemas. The resulting numerical outputs feed directly into analytical engines that calculate metric velocities, symptom frequencies, and treatment adherence probabilities.
Advanced phonetic transformation pipelines achieve sub-second latency conversions, translating complex multi-speaker clinical dialogues into structured JSON payloads ready for immediate dashboard rendering.
To comprehensively illustrate how disparate audio inputs systematically evolve into distinct visual formats through specialized algorithmic parsing, the following reference framework maps the end-to-end transformation topology.
| Audio Input Type | Parsing Algorithm | Resulting Data Points | Visualization Format |
|---|---|---|---|
| Multispeaker Clinical Encounter | Diadactic Neural Speaker Diarization | Talk-to-listen ratios, interruption frequencies | Interactive Timeline Gantt Chart |
| Pharmacological Consultation | Biomedical Named Entity Recognition | Dosage frequencies, contraindication flags | Hierarchical Heatmap Grid |
| Emergency Triage Monologue | Acoustic Prosody and Velocity Analyzer | Speech tempo, vocal strain indices, urgency scores | Radial Velocity Gauge Meter |
| Longitudinal Chronic Care Check-in | Long Short-Term Memory Sentiment Engine | Patient sentiment drift, adherence confidence | Multi-variate Trend Line Graph |
Linguistic patterns converting into visual telemetry
The translation of human speech into vibrant visual telemetry represents a profound intersection of linguistics, mathematics, and cognitive design. When a physician discusses treatment plans with a patient, the spoken narrative is inherently rich with emotional inflection, hesitation markers, and precise medical terminology. Automated transcription platforms capture these nuances not merely as words on a screen, but as behavioral and clinical variables.
For instance, the frequency of hesitant pauses combined with downward inflectional shifts in speech can be mathematically quantified as a hesitancy index. When aggregated across hundreds of oncology consultations, this metric transforms into a glowing scatter plot that highlights patient anxiety hotspots relative to specific chemotherapy regimens.
Furthermore, the semantic density of a conversation—measured by the ratio of specialized clinical terms to conversational filler—serves as a reliable proxy for consultation complexity. Telemetry engines parse this density and feed the computed values directly into visual allocation engines. Complex surgical pre-op briefings naturally generate high-density clusters, which dashboards render as intricate node-link diagrams illustrating topic transitions and information retention risks.
By mapping linguistic cadence, pitch variance, and vocabulary diversity onto Cartesian coordinates, these platforms turn intangible conversations into tangible topographic maps of clinical communication.
Consider the practical deployment of these visualization mechanics within a bustling metropolitan cardiology department, where patient intake interviews are continuously monitored. The telemetry engine detects a sudden uptick in rapid, high-pitch verbal cadences coupled with specific cardiovascular symptom s. The underlying algorithm instantly translates this linguistic pattern into a flashing amber alert widget on the central nursing station dashboard, prompting immediate preventative intervention.
This seamless conversion from acoustic waveform to visual warning exemplifies the immense utility of turning spoken dialogue into structured, real-time spatial awareness.
Healthcare administrators leverage visual telemetry dashboards to uncover hidden operational bottlenecks within clinical workflows

Source: ctfassets.net
Behind the gleaming facades of modern hospitals, clinical operations often move through intricate mazes of patient handoffs, administrative burdens, and unpredictable pacing. Healthcare leaders constantly seek clarity amid this operational complexity, turning to advanced visual telemetry dashboards that cut through the noise of raw data. These sophisticated interfaces render invisible friction points visible, translating mountains of medical charting metadata into intuitive, vibrant displays of clinical reality.
Transforming complex datasets into actionable visual layers allows hospital executives to observe the pulse of their facilities in real time. Instead of relying on retrospective monthly reports, decision-makers view dynamic charts that map the precise flow of patient care from intake to discharge. This immediate visibility empowers administrators to intervene swiftly where delays accumulate, ensuring that resources align seamlessly with patient volume across every department.
Graphical Representations of Consultation Durations
Visualizing the exact duration of clinical consultations reveals systemic scheduling inefficiencies that traditional spreadsheets routinely obscure. When patient encounters are plotted across scatter plots and distribution curves, administrators instantly spot the variance between allotted time slots and actual face-to-face interaction durations. For example, cardiology departments utilizing these graphical layers frequently discover that initial consultations consistently overrun by fourteen minutes, cascading delays into afternoon procedures.
Addressing these discovered scheduling anomalies requires targeted structural adjustments based on empirical time-motion analytics. Hospitals implementing dynamic scheduling models observe remarkable improvements in patient throughput and provider satisfaction.
Autoscriber analytics insights data visualization transforms raw metrics into brilliant clarity, painting a vivid picture of progress. As digital landscapes expand, safeguarding that growth becomes essential, leading teams to utilize a reliable website security dashboard to review gpgaddy to fortify their foundations. Ultimately, this robust protection empowers clearer autoscriber analytics insights data visualization, driving confident, forward-thinking decisions every single day.
- Adjusting appointment template durations from rigid fifteen-minute blocks to flexible twenty-minute intervals for complex initial visits.
- Deploying automated pre-visit digital questionnaires to capture patient histories prior to the physician entering the examination room.
- Reallocating nursing support staff to high-variance clinics during peak morning hours to expedite patient rooming procedures.
- Establishing automated notification systems that alert waiting room coordinators when a consultation exceeds the baseline threshold by more than twenty percent.
Visual Heatmaps Tracking Physician Documentation Fatigue
The burden of electronic health record documentation frequently drives clinical burnout, making the spatial tracking of after-hours charting an essential administrative responsibility. Visual heatmaps overlay shift rotations with timestamped charting activity, painting a striking picture of cognitive exhaustion across hospital floors. Bright crimson intensity zones on these maps explicitly highlight attending physicians spending three or more hours completing medical notes well past midnight, particularly within emergency medicine and intensive care units.
Observing these geographic and temporal zones of fatigue enables hospital leadership to re-engineer shift rotations and documentation workflows before retention rates plummet. Strategic interventions driven by heatmap analytics directly target the root causes of administrative strain.
Operational visualization layers transform abstract clinical exhaustion into undeniable cartographies of fatigue, guiding executive intervention where electronic health record demands intersect with human endurance limits.
Autoscriber analytics insights data visualization uncovers hidden patterns within raw metrics, painting a vivid picture of digital performance. As leaders harness these illuminating dashboards, steering personal narratives requires precision, which you can achieve through kalicube online reputation management for individuals to shape public perception with utmost confidence. Ultimately, these transformative autoscriber analytics insights data visualization tools empower everyone to track growth and inspire lasting success.
Methodology for Establishing Baseline Performance Benchmarks
Accurate operational optimization begins with the rigorous establishment of baseline performance benchmarks derived from historical charting metadata. Data scientists and clinical informaticists extract multi-year archives of electronic health record timestamps, parsing millions of individual interaction events to define normal operational variance. This historical foundation accounts for seasonal surges, such as winter influenza epidemics, ensuring that baseline metrics reflect true operational conditions rather than idealized theoretical capacities.
Establishing these quantitative standards requires a meticulous validation process that incorporates both quantitative server logs and qualitative clinician feedback. Once validated, these benchmarks serve as the foundational bedrock against which all subsequent workflow modifications and technological deployments are measured.
- Extracting twelve months of granular timestamped metadata from core electronic health record systems to capture complete annual operational cycles.
- Normalizing the dataset by filtering out extreme statistical outliers caused by system outages or catastrophic regional health events.
- Segmenting the normalized data by medical specialty, acuity level, and physician seniority to account for inherent differences in clinical workflows.
- Computing median and percentile distributions for key operational milestones, including chart closure times, order entry velocity, and patient dwell durations.
- Publishing the finalized baseline models within interactive executive visualization portals to maintain continuous alignment across clinical and administrative leadership teams.
Optimization Strategies Derived from Operational Visualization Layers
Translating visual telemetry and baseline benchmarks into sustained institutional performance demands a structured, multi-faceted approach to healthcare process engineering. When hospital leadership gains the ability to observe the exact mechanics of clinical workflows through comprehensive graphical interfaces, the path toward meaningful optimization becomes remarkably clear. By examining the interplay between patient volume, documentation latency, and staffing allocations, decision-makers deploy targeted interventions that fundamentally reshape daily hospital operations.
A primary strategy involves the systemic reduction of administrative friction through the intelligent redesign of electronic health record user interfaces tailored specifically to high-latency specialties. For instance, orthopedic surgery departments burdened by repetitive documentation requirements benefit immensely from customized macro templates and voice-to-text integration layers developed directly from visualization insights. Furthermore, nursing workflows undergo continuous refinement as telemetry layers reveal recurring bottlenecks in medication administration handoffs.
Hospitals that actively monitor these visual data streams routinely redirect floating nursing personnel to bottlenecked inpatient units before minor delays compound into severe systemic gridlock.
Resource allocation models also experience a profound evolution, shifting from reactive emergency measures to predictive, data-informed scheduling frameworks. Administrative teams utilize predictive visualization modules to forecast staffing shortages weeks in advance, analyzing historical correlation patterns between weather events, local community health trends, and emergency department admissions. This proactive alignment ensures that physician and nursing rosters maintain optimal nurse-to-patient ratios, mitigating the risk of cognitive overload and preserving clinical accuracy.
Ultimately, the integration of operational visualization layers bridges the historical divide between administrative oversight and clinical reality, fostering a collaborative ecosystem where data-driven insights continuously elevate the standard of patient care delivery.
Clinical documentation intelligence engines utilize sophisticated charting metrics to decode longitudinal patient sentiment shifts.

Source: pickl.ai
Modern healthcare environments increasingly recognize that the cadence of a spoken conversation holds as much diagnostic value as the vital signs displayed on a monitor. Beneath the clinical exchange of symptoms and prognoses lies a rich tapestry of emotional telemetry, waiting to be unlocked by advanced computational frameworks. These innovative engines listen deeply, bridging the gap between raw auditory encounters and actionable psychological insights.
By transforming routine clinical dialogue into structured data, modern platforms empower care teams to track the subtle emotional evolution of individuals over extended periods of healing. This capability shifts medical practice from a reactive model to a proactive, highly personalized continuum of care that respects the human experience behind every diagnosis.
Integration of affective computing measurements within routine physician patient dialogue tracking
The seamless fusion of affective computing into everyday clinical workflows marks a profound leap forward in how healthcare providers understand the human side of medicine. As physicians converse with individuals in exam rooms, ambient listening devices and transcription algorithms work in tandem to capture not just the words spoken, but the underlying emotional resonance. This process involves the careful calibration of vocal biomarkers, speech pacing, and lexical choices to map out the psychological climate of the medical encounter.
Integrating these measurements ensures that the intangible feelings of fear, relief, or uncertainty are no longer lost to the ether of memory, but are instead woven directly into the electronic health record as quantifiable metrics. Care teams can now review trends in emotional stability just as easily as they track blood pressure fluctuations, leading to a more holistic understanding of treatment adherence and recovery barriers.
Affective computing transforms the unspoken emotional undercurrents of the exam room into clear, actionable clinical telemetry that enhances physician empathy and patient trust.
Linguistic indicators signaling patient apprehension during diagnostic disclosures
Pinpointing the exact moments a patient experiences rising anxiety during a heavy diagnostic revelation requires a meticulous linguistic lens. Automated intelligence systems scan transcripts for specific verbal markers that reliably correlate with emotional distress and mental resistance.
Before reviewing the core vocal cues associated with diagnostic anxiety, it is essential to understand that apprehension rarely announces itself loudly; rather, it hides within the micro-structure of everyday speech patterns. The following indicators serve as critical red flags for clinicians navigating sensitive news:
- Sudden truncation of sentence structures, where individuals leave thoughts unfinished or trail off mid-explanation.
- A marked increase in the frequency of lexical fillers such as hesitant pauses, throat-clearing, and repetitive use of qualifying uncertainty phrases.
- A rapid shift toward depersonalized language, substituting direct references to self with generalized or distant pronouns.
- Notable escalation in vocal pitch coupled with a measurable deceleration in speaking tempo as the gravity of the diagnosis sinks in.
Visual dashboard interface displaying emotional trajectory curves over multiple visits
Imagine stepping into a digital command center where the patient’s emotional journey is rendered visible through a luminous, multi-layered visual interface. Upon the high-resolution clinical display, a sophisticated graph materializes, tracing the longitudinal sentiment variation across months of specialized treatment. A gentle turquoise curve undulating across the screen represents baseline tranquility, while sharp, amber dips instantly highlight moments of acute psychological distress experienced during past oncology consultations.
Hovering the cursor over a specific downward inflection point on the timeline reveals a synchronized playback window, juxtaposing the sentiment score against the exact transcript snippet where the apprehension peaked. Color-coded heatmaps pulse gently in the margin, contrasting the initial high-anxiety baseline of the first visit with the gradual, upward stabilization slope observed during subsequent follow-up appointments. This vivid, cinematic visualization allows multidisciplinary care teams to instantly grasp whether a patient is internalizing coping mechanisms or quietly slipping into clinical depression, entirely transforming the empathy-driven architecture of modern medicine.
Clinical relevance of tracking longitudinal sentiment variations through automated charting telemetry
Tracking the longitudinal sentiment variations of patients through automated charting telemetry represents a fundamental transformation in the architecture of chronic disease management and holistic healing. When healthcare providers rely solely on cross-sectional assessments gathered during fleeting clinical encounters, they frequently miss the subtle, progressive psychological erosion that often precedes severe health crises or treatment abandonment. Automated charting engines continuously ingest and decode conversational data across months and years, constructing a continuous emotional ledger that reveals patterns invisible to the naked human eye.
For instance, in real-world cardiology and oncology practices, subtle downward spirals in patient sentiment—characterized by increased hesitant speech, withdrawal, and escalating lexical expressions of hopelessness—often precede medication non-adherence by up to three weeks. By capturing these early warning signals, clinical documentation intelligence engines allow care teams to intervene proactively, deploying targeted psychological support or adjusting communication strategies before the patient spirals into acute distress or emergency room readmission.
Furthermore, this objective tracking of emotional trajectories helps mitigate physician burnout by illuminating the direct therapeutic impact of compassionate communication, thereby reinforcing the profound connection between emotional validation and positive physiological outcomes in everyday clinical practice.
Cross-departmental clinical intelligence relies heavily on synchronized visual storytelling to align multidisciplinary care teams.
Modern healthcare ecosystems thrive when complex auditory encounters captured during patient consultations are instantaneously synthesized and mapped across enterprise information landscapes. Bridging the gap between spoken clinical narratives and tangible administrative action requires sophisticated integration layers that translate raw telemetry into shared organizational perspectives.
Automated note generation systems operate as the foundational bridge connecting raw conversational audio with enterprise electronic health record display layers. As acoustic waves are converted into structured text through advanced natural language processing, middleware application programming interfaces immediately route these parsed variables into interoperable data repositories. These pipelines rely on Fast Healthcare Interoperability Resources standards to ensure that clinical parameters, diagnostic impressions, and treatment plans populate the correct database fields without manual transcription delays.
Once data securely enters the enterprise tier, modern visualization rendering engines ingest these synchronized variables, projecting dynamic graphical charts directly into the physician workspace and nursing station displays. This seamless architectural workflow guarantees that multidisciplinary providers view the exact same patient trajectory insights in real time, fostering unprecedented operational clarity across hospital wings.
Synchronized visual storytelling transforms fragmented departmental records into a single, cohesive narrative of patient care, eliminating dangerous silos in complex health systems.
Departmental Data Integration and Visualization Rendering Architecture
To fully grasp how modern hospitals operationalize clinical intelligence dashboards, examining the direct pathways linking data sources to end-user impact is essential. The following overview details the precise mechanisms driving cross-departmental alignment through responsive graphical frameworks.
| Departmental Data Sources | Visualization Rendering Engines | Target Clinical Audiences | Decision-Making Impacts |
|---|---|---|---|
| Emergency Department Triage Audio | WebGL Vector-Based Spatial Heatmaps | Triage Nurses and Flow Coordinators | Reduces patient wait times by dynamically predicting surge bottlenecks and optimizing bed turnover. |
| Inpatient Rounding Transcripts | D3.js Longitudinal Trend Graphs | Attending Physicians and Pharmacists | Accelerates medication reconciliation and prevents adverse drug events through early symptom tracking. |
| Surgical Suite Debriefing Feeds | SVG Interactive Timeline Dashboards | Surgeons and Operating Room Directors | Enhances surgical throughput and decreases room turnover intervals via rigorous bottleneck analysis. |
| Outpatient Telehealth Recordings | Canvas-Based Sentiment Scatter Plots | Primary Care Teams and Case Managers | Improves chronic disease management compliance through proactive identification of patient distress cues. |
Procedure for Filtering Extraneous Auditory Noise from Clinical Intelligence Visual Outputs
Maintaining the integrity of healthcare visual telemetry demands rigorous protocols to isolate meaningful clinical signal from background ambient interference. Without structured filtering, graphical dashboards risk displaying distorted metrics that could misguide clinical interventions.
- Raw audio streams captured via ambient microphones undergo an initial acoustic threshold screening, where non-speech frequencies and environmental room noise are algorithmically excised before transcription processing begins.
- Natural language understanding modules apply context-aware clinical dictionaries to strip conversational filler, irrelevant pleasantries, and administrative chatter from the parsed text array, retaining solely medically relevant terminology.
- The validated text parameters pass through a rules-based validation filter that cross-references extracted symptoms and orders against established enterprise nomenclature libraries to eliminate spurious artifacts.
- Cleaned data entities are subjected to a confidence-scoring algorithm, ensuring that only data points exceeding a strict statistical certainty threshold are rendered onto the final enterprise visualization dashboard.
Collaborative Workflows Enabled by Unified Graphical Charting Representations
Modern healthcare delivery systems function effectively only when multidisciplinary teams share a unified, unambiguous understanding of patient status and operational flow. When disparate departments such as nursing, pharmacy, laboratory services, and administration view contradictory or delayed information, clinical errors multiply and operational efficiency plummets. Unified graphical charting representations solve this persistent challenge by establishing a single source of visual truth that bridges communication gaps across hospital units.
Through real-time rendering of automated scribe outputs, clinical dashboards translate dense longitudinal narratives into intuitive visual trajectories, empowering disparate specialists to synchronize their interventions instantly.
Consider a large academic medical center managing a complex oncology patient admitted through the emergency department with acute sepsis symptoms. In a traditional operational model, the emergency physician, inpatient hospitalist, oncology specialist, and clinical pharmacist would review fragmented notes, leading to delayed antibiotic administration and fragmented monitoring. With a unified visual intelligence platform active, the ambient transcription engine captures the initial resuscitation dialogue and immediately populates a shared graphical timeline visible across all departmental stations.
The pharmacist observes real-time renal function metrics alongside medication administration graphs, while the nursing supervisor monitors fluid balance trends through color-coded spatial widgets. This shared visual telemetry completely alters team dynamics, shifting communication from reactive status inquiries to proactive, data-driven collaborative planning. Because every provider interacts with the exact same visual narrative, handoff discrepancies vanish, and patient safety metrics improve exponentially across the entire continuum of care.
Predictive charting visualizations forecast future resource allocation requirements based on historical dialogue trends
Modern healthcare systems increasingly rely on advanced data analytics to peer into the clinical future, moving far beyond reactive management into proactive operational readiness. By decoding the vast oceans of spoken interactions captured during routine medical encounters, automated platforms extract actionable intelligence that redefines how hospitals prepare for tomorrow’s challenges.
Sharp autoscriber analytics insights data visualization illuminates hidden patterns, guiding modern enterprises toward breakthrough clarity. By carefully evaluating the lemonway business model strengths weaknesses , forward-thinking leaders uncover crucial operational advantages to fuel sustainable growth. Ultimately, mastering these dynamic metrics through advanced autoscriber analytics insights data visualization transforms raw numbers into a brilliant roadmap for future success.
Through the continuous synthesis of longitudinal audio data and electronic health record repositories, analytical engines construct high-resolution predictive models. These systems identify subtle verbal precursors in patient-provider dialogues—such as escalating frequency of specific symptom mentions or shifting emotional tones—that historically precede high-acuity admissions or extended lengths of stay.
Machine learning forecasting models project seasonal patient volume surges using conversational telemetry
Advanced neural networks ingest years of unstructured consultation transcripts, mapping linguistic markers directly against admission logs to uncover hidden seasonal vectors. When physicians and patients repeatedly discuss specific environmental triggers or localized symptom clusters during routine check-ups, the telemetry engine flags these conversational anomalies weeks before traditional triage metrics register an influx. For instance, respiratory clinics utilizing these algorithms successfully anticipated a severe influenza spike three weeks prior to peak emergency room arrivals by tracking subtle upticks in patient-reported cough frequency and fatigue descriptors during routine telehealth visits.
This early warning mechanism allows hospital executives to dynamically adjust staffing rosters, secure necessary pharmaceutical supplies, and reallocate physical bed capacity before bottlenecks materialize on the clinical floor.
Algorithmic parameters translating spoken clinical intentions into preemptive supply chain visualizations
Transforming ambient voice data into actionable supply chain logistics requires a sophisticated matrix of natural language processing parameters and statistical weighting models. Engineers configure these algorithms to monitor specific clinical commitments, prescription requests, and procedural discussions occurring in real-time across outpatient and inpatient settings. The primary parameters governing this transformation include:
- Conversational frequency weighting, which measures how often specific therapeutic interventions are verbally ordered by attending physicians.
- Temporal velocity indicators, calculating the speed at which a clinical discussion transitions from exploratory diagnosis to definitive treatment planning.
- Sentiment intensity scores, evaluating the urgency and emotional stress embedded within patient-provider dialogues to gauge immediate resource criticality.
- Cross-departmental referral density, mapping the spoken intent for specialist consultations against available departmental bandwidth.
When these parameters converge, they feed directly into dynamic inventory dashboards that automatically adjust procurement orders for surgical kits, personal protective equipment, and specialized medication reserves without requiring manual administrative intervention.
Predictive UI interfaces alerting nursing supervisors about impending departmental capacity constraints
User interface designers translate complex algorithmic outputs into intuitive, glanceable widgets deployed on nursing station monitors and mobile administrative tablets. A prominent visual display features a color-coded capacity heat map that pulses from soothing emerald green to urgent crimson as predictive algorithms detect rising patient acuity and discharge delays.
Real-time conversational telemetry bridges the dangerous gap between reactive crisis management and preemptive clinical orchestration.
Accompanying this heat map, a sliding timeline visualization projects bed occupancy rates across the next seventy-two hours, factoring in both scheduled procedures and unpredicted admissions derived from ongoing triage dialogues. When the system detects an impending threshold breach, a contextual notification panel highlights specific bottlenecks, such as a projected shortage of telemetry-monitored beds, while simultaneously recommending safe early-discharge candidates based on recent physician-patient recovery dialogue summaries.
Strategic advantages of foresight modeling driven by automated encounter charting
Deploying predictive foresight modeling fundamentally alters the economic and clinical viability of modern healthcare delivery networks. By harnessing the untapped wealth of everyday clinical conversations, hospitals transition from a state of perpetual firefighting to one of calm, calculated operational mastery. The strategic dividends of this technological integration manifest across multiple critical dimensions of hospital administration and patient care quality.
Operational efficiency skyrockets as staffing managers align labor supply precisely with anticipated patient demand curves, significantly reducing reliance on expensive agency nurses and mitigating staff burnout caused by unexpected surges. Financially, hospitals optimize inventory holding costs, virtually eliminating both critical shortages of life-saving supplies and the wasteful accumulation of expired pharmaceuticals. Clinically, patient safety improves dramatically because emergency departments and intensive care units maintain optimal nurse-to-patient ratios, ensuring rapid intervention during critical status changes.
Furthermore, executive leadership gains the empirical confidence required for long-term capital allocation, utilizing longitudinal dialogue trends to justify investments in specialized service lines or facility expansions. Ultimately, automated encounter charting transforms routine spoken interactions into a powerful strategic compass, guiding healthcare institutions toward unprecedented levels of resilience, financial stability, and clinical excellence.
Ethical boundaries govern the transformation of sensitive patient dialogues into quantifiable visual metrics.

Source: autoviz.ai
Modern healthcare analytics operate at a profound intersection where intimate human narratives meet cold, calculated digital transformation. As voice-driven clinical data flows into visualization engines, strict moral safeguards must be enforced to protect individual privacy while unlocking population-level insights. Navigating this delicate balance requires an unwavering commitment to patient dignity, ensuring that the pursuit of operational efficiency never compromises the sanctity of the doctor-patient relationship.
The architecture of modern medical transcription platforms relies heavily on safeguarding personal identifiers long before any chart or dashboard renders on a clinical administrator’s screen. Advanced engineering teams deploy rigorous protocols to strip away vulnerability at the foundational layer of data ingestion. This visualization of clinical reality demands absolute transparency, robust cryptographic shields, and a cultural dedication to ethical stewardship across every multidisciplinary healthcare network.
Cryptographic masking procedures applied to phonetic data prior to dashboard rendering
Before raw acoustic waves and spoken utterances translate into vibrant operational heatmaps or bar charts, automated pipelines execute multi-layered cryptographic transformations. Phonetic streams undergo immediate tokenization, replacing identifiable voiceprints and verbal markers with randomized cryptographic hashes that retain acoustic statistical properties without exposing human identity. Advanced differential privacy algorithms inject controlled mathematical noise into the dataset, ensuring that individual patient trajectories remain completely obscure to unauthorized viewers while preserving the overarching trends required for institutional resource planning and workflow optimization.
Visualizing these masked data points involves rendering high-contrast vector graphics where axes represent generalized clinical timeframes rather than specific patient appointments. Color-coded risk matrices display aggregated burnout indicators or diagnostic delays strictly through anonymized scalar values. Security architects utilize homomorphic encryption standards, allowing analytics engines to compute complex mathematical correlations directly on encrypted phonetic tokens without ever decrypting the underlying sensitive health information.
Governance frameworks ensuring patient anonymity within aggregated clinical telemetry charts, Autoscriber analytics insights data visualization
Institutional oversight committees enforce stringent governance policies to prevent the re-identification of patients within large-scale telemetry dashboards. These frameworks mandate strict cell-suppression rules, meaning any data point representing a cohort smaller than a statistically significant threshold is automatically blurred or omitted from visual reporting. By combining role-based access controls with continuous automated compliance auditing, healthcare systems maintain an impenetrable barrier between high-level operational dashboards and underlying electronic health records.
To fully understand the structural integrity of these privacy defenses, healthcare institutions rely on standardized mitigation strategies and regulatory benchmarks. The matrix below Artikels the core vulnerabilities inherent in clinical data visualization alongside the corresponding defense mechanisms, regulatory requirements, and oversight frequencies utilized by top-tier medical facilities.
| Privacy Vulnerabilities | Mitigation Protocols | Compliance Standards | Auditing Frequencies |
|---|---|---|---|
| Acoustic re-identification via unique vocal cadence | Phonetic tokenization and differential noise injection | HIPAA Safe Harbor Method & GDPR Article 32 | Real-time automated logging with monthly manual reviews |
| Cross-database correlation attacks | k-anonymity enforcement and data cell suppression | HITECH Act & ISO/IEC 27701 | Quarterly vulnerability penetration testing |
| Unauthorized insider dashboard access | Multi-factor authentication and role-based masking | SOC 2 Type II Trust Services Criteria | Continuous monitoring and bi-annual compliance audits |
| Metadata leakage through timestamp clustering | Temporal jitter and generalized date bucketing | NIST Special Publication 800-53 | Monthly configuration and log analysis |
Balancing comprehensive operational visibility and stringent patient confidentiality
Achieving total operational transparency while upholding absolute patient confidentiality is the ultimate paradox of modern healthcare administration. Hospital executives urgently need granular insights into patient wait times, clinician communication bottlenecks, and resource allocation efficiency to prevent system overloads, yet every data point harvested originates from deeply vulnerable human experiences. Striking this balance requires moving beyond basic compliance checklists and adopting a philosophy of ethical data minimalism, where systems only process and display the exact volume of information necessary to solve a specific operational challenge.
Consider the real-world deployment of integrated communication dashboards at Mayo Clinic or Cleveland Clinic, where emergency department patient flow and clinical dialogue sentiment are monitored in real time. Administrators can instantly visualize spikes in patient anxiety or departmental friction without ever viewing a patient’s name, medical record number, or distinct vocal inflection. This level of systemic visibility transforms chaotic emergency rooms into predictable, streamlined environments through aggregated metadata.
When governance protocols are flawlessly integrated with advanced cryptographic masking, healthcare organizations can achieve high-performance operational intelligence while honoring the sacred trust placed in them by every individual seeking care.
True clinical telemetry achieves its highest purpose when operational excellence and absolute patient privacy exist in perfect, unbreakable harmony.
Last Word: Autoscriber Analytics Insights Data Visualization
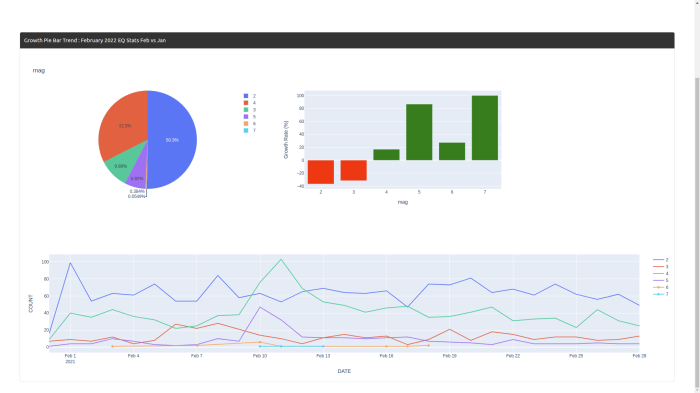
Source: githubusercontent.com
Ultimately, the journey from spoken dialogue to brilliant graphical intelligence represents a monumental leap forward for modern medicine. By harmonizing rigorous cryptographic governance with predictive forecasting and collaborative storytelling, these advanced visual frameworks illuminate a path toward unprecedented clinical excellence. As healthcare providers embrace these transformative tools, they unlock a future where every conversation builds a stronger, more resilient, and deeply empathetic healing environment.
