Primary care ehr stands at the vital intersection of daily medical practice and technological innovation, quietly shaping the rhythm of modern healing spaces. Beneath the fluorescent lights of busy morning clinics, dedicated physicians routinely wrestle with the invisible friction of digital documentation, discovering that every click and keystroke holds profound weight for patient outcomes.
As the healthcare landscape rapidly transforms, the journey through outpatient software demands resilience, sharp focus, and a deep commitment to human-centric care. Every interface design choice, acoustic boundary, and data synchronization protocol directly influences how medical professionals connect with the individuals who walk through their doors seeking relief and reassurance.
Navigating Outpatient Software Bottlenecks During Hectic Morning Schedules
Morning rounds in primary care begin with a relentless surge of clinical demands, where general practitioners face a labyrinth of digital interfaces that often impede rather than assist patient care. Amidst the hurried footsteps and waiting rooms filled with anxious patients, the modern clinician sits before a glowing monitor, locked in a silent struggle against counterintuitive outpatient software. This daily friction turns simple chart reviews into exhausting mental hurdles, threatening the very flow of healing.
The psychological friction experienced by general practitioners when transitioning between different patient documentation screens is profound and pervasive. Every click required to jump from a medication reconciliation tab to a previous progress note introduces a micro-interruption that disrupts the clinician’s train of thought. This constant context-switching demands active cognitive readjustment, draining mental bandwidth that should rightfully be dedicated to clinical reasoning and empathetic patient communication.
Instead of maintaining a seamless narrative of the patient’s health journey, the physician is forced to act as a data entry clerk, mentally stitching together fragmented windows of information scattered across poorly designed digital dashboards. Over time, this administrative drag accumulates into severe mental exhaustion, transforming the morning schedule into a grueling marathon of endurance against the very tools meant to lighten the load.
Visual Fatigue Degrading Diagnostic Accuracy Over Long Shifts
Staring at monochromatic, densely packed electronic health record interfaces for eight to ten hours daily places an immense physiological toll on the human visual system, directly impacting clinical judgment. As the hours tick away, constant accommodation and convergence required to parse low-contrast text, tiny icons, and cluttered data fields lead to asthenopia, commonly known as eyestrain. This persistent visual strain triggers physical symptoms such as blurred vision, headaches, and neck stiffness, which subtly chip away at the practitioner’s concentration and patience.
When the eyes struggle to process visual stimuli efficiently, the brain compensates by allocating fewer resources to complex analytical tasks, creating a dangerous vulnerability in high-stakes environments. Subtle clinical cues embedded within lab trends or medication histories can easily be glossed over when a tired mind tries to make sense of a blinding white interface awash in unformatted data. Furthermore, prolonged exposure to harsh screen glare disrupts normal circadian rhythms and accelerates mental fatigue, compounding the risk of diagnostic oversight.
Research in human factors engineering consistently demonstrates that cumulative visual strain degrades pattern recognition capabilities, leading to missed diagnoses and delayed interventions during the latter half of a grueling shift. Restoring clarity to the digital workspace is therefore not merely an aesthetic preference, but an absolute clinical imperative to safeguard patient safety and preserve the cognitive sharpness of healthcare providers.
To better understand how specific interface deficiencies translate into operational hurdles, the following matrix Artikels the primary friction points encountered during daily workflows, their corresponding cognitive impact ratings on a standard scale, and actionable mitigation strategies derived from human-centered design principles.
| Interface Friction Point | Cognitive Impact Rating | Mitigation Strategy |
|---|---|---|
| Buried lab trend graphs requiring multiple clicks to view | High (8.5/10) | Implement customizable side-by-side split screens with persistent longitudinal data views. |
| Non-standardized medication allergy alerts prompting frequent overrides | Severe (9.2/10) | Deploy intelligent alert filtering based on clinical relevance and severity grading. |
| Rigid template structures that enforce linear data entry | Moderate (6.8/10) | Incorporate flexible, voice-activated documentation assistants and customizable macros. |
Physical workspace ergonomics play a decisive role in determining how rapidly a clinician can navigate software screens while maintaining physical comfort throughout the day. Positioning the primary monitor at exact eye level, roughly an arm’s length away, prevents the chronic cervical strain that forces physicians to constantly readjust their posture while scanning dense clinical records. Furthermore, utilizing high-resolution, anti-glare curved displays significantly widens the effective field of view, allowing practitioners to keep reference charts and active documentation windows open simultaneously without excessive window toggling.
The physical layout of input devices matters immensely as well; an ergonomic mouse paired with a customized macro-enabled keyboard drastically reduces repetitive wrist motion and minimizes the physical distance the hand must travel to execute frequent commands. When the physical workstation is meticulously calibrated to human biomechanics, screen navigation transforms from a cumbersome physical chore into a fluid, almost instinctive extension of the clinician’s thought process, ultimately reclaiming precious minutes for direct patient engagement.
“True technological advancement in healthcare is measured not by how much data a system can capture, but by how effortlessly it protects the cognitive wellbeing and focus of the healing professional.”
Digital health platforms must quietly harmonize ambient acoustics with privacy mandates inside examination rooms.
Morning light filters through the blinds of a bustling urban clinic, where the quiet rhythm of healing now relies on an invisible digital dance. Inside the examination room, the modern stethoscope is no longer just cold metal, but a sophisticated network of microphones and neural networks designed to capture every heartbeat of the patient encounter. As clinicians engage in deeply personal dialogues with those seeking care, advanced digital health platforms work tirelessly in the background.
These systems must achieve a delicate equilibrium, capturing the subtle cadence of human speech while fiercely guarding the sacred trust of medical confidentiality against the backdrop of a noisy, high-pressure medical environment.
Speech-to-text algorithms deployed in contemporary clinical settings utilize advanced neural beamforming and acoustic echo cancellation to isolate the physician’s and patient’s voices from disruptive background sounds. These intelligent models are trained on vast auditory landscapes, allowing them to instantly distinguish between the rustling of medical charts, the hum of fluorescent lighting, and the crucial articulation of symptoms. By filtering out ambient interference at the hardware and software intersection, the transcription engine ensures that only medically relevant dialogue is processed.
This technological precision transforms chaotic auditory environments into pristine, structured data streams without requiring the physician to awkwardly repeat phrases or lean uncomfortably close to a recording device.
Balancing automated documentation and regulatory compliance frameworks
The integration of automated note-taking within the confines of the examination room represents a profound shift in clinical workflow, yet it must operate under the unyielding umbrella of healthcare privacy laws such as HIPAA and GDPR. Every spoken word converted into digital text constitutes sensitive protected health information that requires rigorous lifecycle management. Software developers must ensure that speech processing occurs either entirely on secure local hardware or through zero-retention cloud pipelines where voice data is instantly scrubbed the moment transcription concludes.
This approach prevents third-party model training on private patient conversations, aligning cutting-edge convenience with absolute legal compliance.
Compliance also extends to patient autonomy and informed consent, requiring transparent communication regarding how voice data is captured and interpreted. Clinical institutions frequently deploy visual indicators—such as subtle LED rings on ambient wall pucks—to signal when active transcription is engaged, empowering patients to pause the digital scribe at any moment during sensitive discussions. Furthermore, automated audit trails log every instance of voice-to-text generation, creating an immutable record of access that satisfies regulatory demands for accountability.
When an algorithm drafts the clinical narrative, the ultimate responsibility for data integrity remains firmly with the human practitioner, who must review and sign off on every generated note before it enters the permanent electronic health record.
Maintaining this intricate balance demands architectural foresight, where security is woven into the very fabric of the acoustic capture process. A striking visual mental image captures this reality: a sleek, minimalist acoustic sensor mounted discreetly on a neutral-toned clinic wall, pulsing with a gentle, reassuring blue light that signifies encrypted data packets flowing silently through a hardened local network, completely shielded from external intrusion.
True digital transformation in medicine respects the intimacy of the exam room just as much as it respects the power of data.
Achieving optimal sound capture while preserving spatial privacy requires intentional physical and digital modifications to the clinical environment. The following strategies Artikel essential methods for refining room acoustics to support accurate transcription without compromising confidentiality.
- Strategic placement of directional boundary microphones near the primary consultation zone to naturally attenuate outside hallway noise.
- Application of sound-absorbing acoustic wall panels and solid core doors to prevent confidential dialogue from bleeding into adjacent waiting areas.
- Implementation of localized white noise generators near doorways to mask speech frequencies effectively for anyone standing outside the room.
- Regular calibration of software gain controls to ensure the system prioritizes close-proximity speech over distant, ambient disturbances.
Cryptographic safeguards for voice-derived medical transcripts
Once spoken dialogue successfully transforms into digital text within the examination room, transmitting that sensitive payload across local networks demands military-grade cryptographic protocols. Voice-derived medical transcripts are uniquely vulnerable during transit from the room-based capture device to the local server or secure cloud repository. To thwart potential interception, modern digital health platforms mandate the use of Transport Layer Security version 1.3 for all internal data pathways.
Additionally, payloads are encrypted at the application layer using Advanced Encryption Standard with 256-bit keys before leaving the local hardware boundary, ensuring that even if a packet is intercepted on the clinic network, it remains entirely unreadable ciphertext.
Network security architecture within modern clinics often segregates medical internet-of-things devices onto isolated virtual local area networks, restricting lateral movement for any compromised endpoint. Real-world implementations in major hospital networks demonstrate that combining hardware-level Trusted Platform Modules with end-to-end encryption successfully prevents unauthorized data exfiltration during high-volume morning rushes. These multi-layered defenses guarantee that the vulnerable window between spoken word and encrypted database entry is virtually nonexistent, preserving patient trust in an increasingly interconnected medical ecosystem.
Solo medical practitioners balance financial sustainability differently from sprawling hospital networks when selecting patient database tools.
When the morning sun cuts across a modest waiting room, the solitary physician does not just examine symptoms; they audit a fragile economic ecosystem. While sprawling health systems absorb enterprise software costs through sprawling bureaucratic budgets, independent clinics operate on a razor-thin margin where every single technology dollar directly impacts patient care quality.
Navigating the fiscal realities of electronic health records requires a meticulous balancing act between immediate cash flow preservation and the absolute necessity of secure, reliable data infrastructure. Every fiscal choice carries a profound weight, dictating whether a community clinic can afford to upgrade its diagnostic tools or hire essential front-desk support.
Financial Realities of Infrastructure Investment
Independent medical offices must weigh the predictable monthly predictability of modern software-as-a-service models against the hefty, localized control of on-premise hardware. Upfront licensing fees for local servers demand substantial capital expenditure, often running into tens of thousands of dollars before a single patient file is digitized, whereas cloud-hosted platforms distribute this burden through manageable subscription fees.
However, the long-term maintenance overhead paints a different picture of fiscal endurance. Local servers require dedicated physical space, climate-controlled environments, and specialized IT contractors to manage manual backups and security patches. Conversely, cloud infrastructure shifts the burden of maintenance, cybersecurity updates, and redundant data storage to the vendor, transforming unpredictable capital expenditures into steady operational expenses that align seamlessly with monthly patient volume fluctuations.
Budget allocation strategies for independent medical offices require a disciplined approach to forecasting both visible and invisible technology expenses over a five-year horizon. Solo practitioners cannot afford the luxury of trial and error when selecting digital tools, making thorough financial planning an absolute cornerstone of modern clinical longevity.
- Capital expenditure planning must account for rapid hardware depreciation cycles, typically forcing server replacements every three to five years to maintain compatibility with evolving medical software standards.
- Subscription model predictability protects independent cash flow, ensuring that monthly operational budgets remain stable even during seasonal dips in patient visits or unexpected reimbursement delays.
- Contingency reserves must be explicitly earmarked for sudden internet outages, emergency data recovery protocols, and vendor price adjustments that frequently catch unprepared clinics off guard.
- Strategic phased deployments allow smaller practices to adopt core clinical modules first, spreading out the cumulative financial impact of comprehensive EHR integration over multiple fiscal quarters.
Strategic technology budgeting in independent medicine is not merely an IT decision; it is the fundamental guarantor of clinical independence and financial resilience.
Comparative Analysis of Practice Infrastructure Investments
Understanding the stark differences between deployment models requires a granular look at the financial commitments demanded across various operational categories. The following matrix illustrates the distinct fiscal profiles independent clinics navigate when building their technological foundation.
| Infrastructure Category | Hardware Investments | Subscription Models | Staff Training Expenditures | Unexpected Downtime Expenses |
|---|---|---|---|---|
| Cloud-Hosted Platforms | Minimal local hardware needed; relies on existing terminals and secure browsers. | Predictable monthly or annual per-user fees covering updates and cloud storage. | Ongoing virtual modules and vendor-provided webinars requiring minimal disruption. | Mitigated by vendor redundancy, though dependent on reliable local internet access. |
| Local Server Infrastructure | High initial outlay for physical servers, backup drives, and secure local networking gear. | Occasional software license renewals and mandatory feature upgrade purchases. | Intensive initial classroom sessions and specialized IT consultant onboarding fees. | Significant potential costs involving localized hardware failure and manual chart recovery. |
Hidden Administrative Costs of Legacy Data Migration
Transitioning decades of paper charts, filing cabinets, and legacy desktop databases into a streamlined modern EHR system involves far more than simply purchasing software licenses. The administrative friction of data migration often bleeds financial resources through lost staff productivity, transcription errors, and the tedious physical scanning of historical patient records.
When clinics move mountains of paper into the cloud, administrative staff are frequently pulled away from patient-facing duties to manually verify demographic data, clean up duplicate patient identifiers, and format historical clinical notes to meet current interoperability standards. This hidden labor represents a substantial drain on practice resources, frequently exceeding the initial software procurement estimates by a considerable margin. For instance, a two-physician family practice transitioning five years of paper archives might easily absorb hundreds of hours of overtime or require temporary administrative staffing to prevent front-office gridlock during the migration window.
Pediatric immunization tracking demands specialized chronological visualization that standard adult-centric charting layouts fail to provide.

Source: himcos.com
Modern pediatric medicine requires a profound departure from traditional electronic health record designs that were originally built for adult internal medicine. When infants enter the clinic, their developmental velocity dictates a hyper-compressed timeline of immunological milestones that standard horizontal grids simply cannot accommodate without risking oversight. Healthcare providers need interfaces that translate complex multi-dose vaccine schedules into intuitive, age-based visual pathways, ensuring that tiny patients receive critical biologics precisely within their narrow windows of efficacy.
Modern primary care ehr systems illuminate the path toward healing, painting vibrant pictures of organized clinics where patient stories unfold seamlessly. Just as industry landscapes shift dynamically, particularly when leap legal software acquired by new ownership sparks fresh innovation, healthcare technology similarly transforms. Ultimately, these brilliant digital advancements empower dedicated providers to champion wellness and illuminate brighter tomorrows for every patient.
Charting multi-dose vaccine schedules across rapid developmental milestones demands a meticulous layout architecture that prioritizes vertical age progression over episodic encounter dates. The exact interface requirements dictate a dynamic, time-scaled matrix where the X-axis represents chronological maturation—measured meticulously in weeks, months, and early years—while the Y-axis categorizes biological antigen families. As a child transitions from neonate to toddler, the software must automatically adjust its visualization density, expanding the critical first twenty-four months into a prominent, high-resolution workspace while compressing later adolescent booster phases.
This layout relies on color-coded interval brackets that signal minimum age thresholds, absolute grace periods, and overdue markers in real time. Furthermore, the system must incorporate interactive dosing nodes that expand upon touch, revealing lot numbers, anatomical injection sites, and parental consent logs without requiring clinicians to navigate away from the primary chronological view. By anchoring clinical documentation to developmental age rather than static calendar dates, the software aligns perfectly with the cognitive workflow of pediatricians who assess health through the lens of growth.
Graphical growth integration with immunization timeline alerts
The convergence of anthropometric tracking and prophylactic scheduling represents one of the most vital engineering achievements in modern ambulatory pediatric software. When a practitioner opens a digital chart, the interface simultaneously renders a longitudinal growth curve—tracking weight-for-age, length-for-age, and head circumference—directly alongside a synchronized immunization timeline. This dual-stream visualization operates on a shared chronological axis, allowing the clinician to instantly correlate physical developmental spurts or faltering growth patterns with upcoming or recently administered vaccine doses.
For example, if an infant’s weight curve demonstrates a sudden deceleration around the four-month mark, the software dynamically highlights the corresponding immunization node for the DTaP and PCV13 series, prompting the clinician to evaluate potential systemic inflammation or underlying nutritional deficits before proceeding with the next round of live or inactivated antigens. Background algorithms continuously cross-reference the child’s exact physical parameters with the latest Advisory Committee on Immunization Practices guidelines, projecting upcoming vaccine windows directly onto the graphical growth trajectory as semi-transparent predictive bands.
If a child falls behind schedule due to an acute illness, the system automatically recalculates the optimal catch-up trajectory, reshaping the visual timeline alerts to reflect the newly adjusted minimum intervals between doses. This seamless fusion eliminates the cognitive friction of toggling between disparate charting modules, transforming raw biometric data and immunization histories into a unified, actionable narrative of a child’s early health journey.
Through this sophisticated alignment, clinicians can visualize both biological maturation and immunological protection in a single glance, drastically reducing the margin for human error during hectic clinical hours.
Precise chronological visualization transforms complex vaccine schedules and biometric trajectories into a unified narrative of early childhood development.
Specialized charting methodologies are essential for managing the intricate variables of pediatric immunization, particularly when dealing with premature infants, underlying chronic conditions, or interrupted series. The following structured parameters Artikel the core functional requirements for advanced pediatric clinical documentation:
- Corrected gestational age calculations for preterm infants, which automatically shift the baseline parameters for primary immunization series to prevent premature or delayed administration of sensitive antigens.
- Conditional logic pathways that adapt to contraindications and precautions, instantly suppressing specific vaccine recommendations and suggesting alternative formulations based on reported adverse reactions or documented immunosuppression.
- Batch-processing capabilities for public health vaccine registry reporting, enabling seamless state-level data synchronization that complies with stringent interoperability standards without adding administrative burden to the clinical encounter.
- Lot-level inventory tracking linked directly to administration charting, ensuring immediate recall management and precise expiration monitoring for multidose vials stored in clinic refrigerators.
The clinic room is quiet save for the gentle hum of ambient white noise, where a dedicated pediatrician holds a lightweight tablet device, reviewing the intricate immunization history of a lively fifteen-month-old toddler. On the high-resolution screen, a vibrant, multi-layered chronological interface displays the child’s entire vaccination journey from birth, mapping each completed dose as a glowing green node along a fluid, color-coded developmental timeline.
Modern primary care ehr systems illuminate patient pathways like digital lighthouses guiding clinical decisions. Just as navigating clinical workflows demands precision, evaluating platforms through a detailed getresponse vs mailchimp analysis empowers organizations to optimize communication strategies with striking clarity. Ultimately, mastering these integrated digital connections breathes new life into primary care ehr networks, fostering enduring community wellness.
With a simple swipe of a thumb, the practitioner expands the current milestone cluster, instantly revealing the exact anatomical site of the previous month’s intramuscular injection alongside the corresponding lot number and batch expiration data. Directly adjacent to this immunization pathway, a synchronized growth curve pulses softly, illustrating a steady, healthy upward trajectory in weight and stature that reassures the clinician of the toddler’s robust overall development.
When the pediatrician taps on an upcoming booster node, a subtle, pulsating alert box appears, displaying the precise minimum permissible interval and flagging a mild upper respiratory infection recorded during the previous week as a momentary point of consideration. The visual layout adapts fluidly to the touch input, decluttering extraneous historical data to focus intensely on the immediate therapeutic window, allowing the physician to converse naturally with the anxious parents while maintaining total mastery over the complex clinical record.
Interoperability protocols often break down silent data handoffs for chronic disease histories

Source: anisolutions.com
Inside the fast-paced ecosystem of modern ambulatory healthcare, the silent fracturing of patient histories during digital transitions represents a critical threat to continuity of care. When a patient suffering from long-term comorbidities moves between disparate electronic health record environments, the expected digital harmony frequently dissolves into fragmented data packets. Physicians stepping into their consultation rooms rely heavily on uninterrupted data streams, yet foundational communication barriers consistently disrupt the transmission of vital longitudinal records.
This invisible breakdown stems from deeply rooted technical disparities across competing vendor infrastructures. As primary care clinics strive to coordinate specialized interventions, the underlying software engines often speak mutually unintelligible digital languages. Consequently, critical diagnostic markers vanish or transform incorrectly during system-to-system migrations, leaving clinical teams blind to historical treatment trajectories and introducing profound risks to patient safety.
Digital Translation Failures During Patient Referral Handoffs
The journey of a patient referral frequently encounters severe digital turbulence the moment information crosses proprietary network boundaries. Common data corruption patterns emerge silently, bypassing standard system alerts and presenting clinicians with altered or incomplete diagnostic profiles. This silent degradation typically manifests as truncated medication lists, misaligned laboratory result timestamps, and stripped diagnostic tags that strip context away from critical longitudinal trends.
When distinct digital platforms attempt to parse incoming information payloads, missing schema definitions lead to automatic field dropping. For instance, a diabetic patient’s continuous glucose monitoring history transferred from a specialty endocrinology portal to a general practitioner suite might lose its specific high-low threshold markers. Healthcare administrators face this frustrating reality daily, where vital clinical narratives disintegrate into isolated, uncontextualized data points.
To visualize this digital fracture, imagine a high-resolution panoramic photograph being forcibly compressed into a low-pixel thumbnail; sharp boundaries blur, color gradients flatten, and essential details disappear entirely. Similarly, sophisticated XML or JSON payloads encounter legacy interface engines that lack the capacity to interpret modern healthcare data standards. The following structural breakdown maps out these critical translation anomalies, detailing the exact metrics at risk alongside the engineering defenses required to preserve clinical fidelity.
| Data Translation Error | Affected Clinical Metrics | Preventative Validation Protocols |
|---|---|---|
| Schema Mapping Desynchronization | Glycated Hemoglobin (HbA1c) trends and Blood Pressure historical logs | Implement strict JSON schema validation checks prior to payload ingestion |
| Timestamp Epoch Conversion Failures | Medication administration schedules and Dosage frequency markers | Enforce ISO 8601 universal time standard formatting across all API endpoints |
| UTF-8 Character Encoding Stripping | Allergic reaction notes and Special clinical narrative instructions | Mandate explicit UTF-8 header declarations and character sanitization filters |
Standardized Communication Syntax for Cross-Platform Synchronization, Primary care ehr
Achieving absolute data integrity during the transit of chronic disease management histories requires strict adherence to uniform communication syntaxes. Modern ambulatory care environments must move beyond proprietary workarounds and fully embrace standardized data exchange frameworks. The integration of Fast Healthcare Interoperability Resources (FHIR) protocols establishes a reliable common ground, ensuring that physiological parameters maintain their exact meaning regardless of the originating or receiving software vendor.
Successful cross-platform synchronization relies on consistent RESTful API architectures combined with structured resource profiling. When transmitting vital sign trends—such as fluctuating blood pressure readings, serial body weight measurements, and oxygen saturation percentages—the data payload must encapsulate precise units of measurement, standardized observation codes, and immutable patient identifiers. Without this rigorous structural discipline, receiving systems default to erroneous interpretations that can severely compromise clinical decision-making processes.
Medical software developers and clinical informatics specialists must work in tandem to eliminate systemic communication gaps. By enforcing strict payload validation routines at both the sending and receiving gateways, healthcare organizations can finally put an end to silent data corruption. The establishment of these rigorous protocols guarantees that every historical data point remains as accurate and actionable inside the receiving clinic as it was at the moment of initial collection.
Front desk triage staff rely on rapid visual indicators to prioritize incoming acute illness complaints in waiting rooms.: Primary Care Ehr
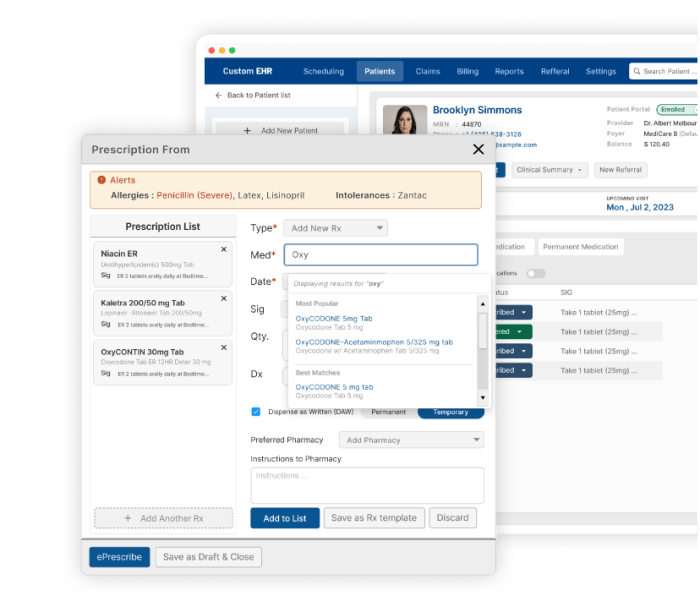
Source: thinkitive.com
The reception area serves as the critical nerve center of any outpatient clinic, where administrative welcoming seamlessly intersects with rapid clinical assessment. When doors open for the morning rush, front desk professionals face a mosaic of human need, translating anxious footsteps and muffled coughs into actionable clinical data before a stethoscope ever touches a patient.
Modern ambulatory electronic health record systems empower front-line teams through sophisticated color-coded urgency algorithms embedded directly into digital check-in dashboards. Receptionists scan incoming arrivals and instantly assign visual tiers—often glowing red for immediate resuscitation needs, amber for urgent acute distress, and green for routine chronic check-ins—translating fleeting symptoms into prioritized queue positions. This digital triage architecture bridges the gap between the chaotic waiting room and the structured clinical back-office, ensuring that critical vital signs capture matches the true physiological risk of the individual sitting just feet away from the counter.
Operational pathways bridging initial arrival and clinical rooming
The operational cadence from the moment a patient approaches the registration desk to their placement inside an examination room requires synchronized choreography among administrative and clinical personnel. As an individual checks in, the receptionist simultaneously initiates an electronic encounter, logging preliminary chief complaints that automatically trigger designated workflow routing within the electronic health record. For instance, in high-volume pediatric clinics utilizing integrated queue management, a patient presenting with respiratory distress immediately bypasses standard registration queues, sending an audible visual alert to the nearest triage nurse terminal.
Medical assistants monitor these real-time dashboard queues constantly, stepping out to escort patients directly to intake bays while bypassing traditional waiting room bottlenecks. This streamlined transition relies heavily on automated digital handoffs, eliminating the traditional paper clip system that historically caused dangerous delays in urgent care delivery. Real-world implementations in large outpatient networks demonstrate that reducing this handoff window from twelve minutes down to under three minutes significantly decreases adverse incident rates in waiting areas.
Consequently, staff training focuses heavily on rapid data entry accuracy during the initial thirty seconds of patient contact, ensuring that downstream clinical teams receive precise, uncompromised information the instant the rooming process begins.
Multidisciplinary communication protocols for emergency patient handoffs
Clear, concise, and structured communication channels prevent clinical errors during high-stress patient handoffs, safeguarding vulnerable individuals as they transition from administrative custody to clinical evaluation. Receptionists, medical assistants, and attending physicians must rely on standardized verbal and digital exchange methods to maintain situational awareness across the entire facility.
- Executing closed-loop verbal read-backs during emergency alerts to confirm that clinical staff have accurately received critical patient location data.
- Utilizing instant messaging overlays within the electronic health record to silently flag deteriorating patients without causing panic in the public waiting area.
- Conducting brief morning safety huddles where front desk staff and triage nurses review expected high-risk appointments and acute capacity limits.
- Applying standardized situation-background-assessment-recommendation frameworks during verbal escalations from reception desk to physician workspaces.
Behavioral indicators of pediatric distress observed prior to vital sign acquisition
Observing pre-verbal infants and young children requires acute visual literacy, as receptionists frequently detect hidden deterioration long before standard thermometers or pulse oximeters are applied. Healthcare facilities train their front-line personnel to look beyond simple crying or restlessness, focusing instead on profound physiological and neurological clues. A child exhibiting abnormal lethargy, a distinct paradoxical breathing pattern where the chest pulls inward during inhalation, or a failure to make eye contact with caregivers presents an immediate red flag that transcends routine waiting room protocols.
Furthermore, subtle nuances such as a high-pitched, inconsolable whine accompanied by mottled skin coloration provide vital clues regarding impending septic shock or severe dehydration. Receptionists observe these behavioral anomalies within seconds of the family entering the facility, immediately overriding standard queue protocols to transition the child into a secured clinical zone. Visual descriptions of these moments highlight a delicate interplay of human intuition and digital speed, where a receptionist’s trained eye acts as the ultimate safeguard for pediatric populations unable to articulate their own internal suffering.
Swift visual identification paired with instant digital categorization remains the single most effective barrier against preventable adverse events during outpatient waiting room bottlenecks.
Patient portal engagement metrics reveal stark behavioral divides across different socioeconomic and generational demographics
Modern healthcare delivery increasingly relies on digital gateways to connect clinical teams with the people they serve, yet cold analytics continuously expose a profound chasm in daily usage patterns. Behind the sleek interfaces of modern patient applications lies a reality defined by steep learning curves, hardware limitations, and stark inequalities that disproportionately affect older and economically disadvantaged populations. Clinics striving for meaningful connection must look past aggregate numbers to confront the genuine friction points keeping vulnerable individuals from accessing their own health data.
The journey from a clinic-generated laboratory report to a patient’s smartphone screen is fraught with invisible barriers that test the patience of even tech-savvy individuals. For seniors and marginalized communities, these digital hurdles often transform routine health management into an insurmountable daily obstacle. Addressing these disparities requires a clear-eyed examination of how hardware, interface design, and foundational skills intersect within real-world healthcare environments.
Digital Literacy Barriers Within Vulnerable Patient Populations
Examining the daily realities of elderly patients attempting to review lab results on mobile devices reveals a cascade of frustrating usability bottlenecks. Tiny font scaling, low-contrast color palettes, and convoluted multi-step authentication processes routinely lock out individuals with declining visual acuity or motor dexterity. Furthermore, reliance on proprietary smartphone apps often assumes uninterrupted high-speed internet access and modern hardware, luxuries that are frequently out of reach for lower-income households.
Modern primary care ehr systems illuminate clinical paths with striking digital clarity, transforming chaotic patient notes into vibrant, organized landscapes of healing. Streamlining daily clinic communication through the nextail email format empowers dedicated healthcare teams to coordinate urgent messages with remarkable precision and professional grace. Ultimately, this seamless connectivity elevates primary care ehr technology, inspiring renewed hope and better health outcomes for every community.
When an octogenarian stares at a glowing screen filled with dense medical jargon and complex numerical ranges, the promise of patient empowerment quickly evaporates into feelings of alienation and anxiety.
Educational deficits compound these interface challenges, as many older adults never developed the foundational digital competencies required to navigate modern software ecosystems. Text-heavy password recovery loops and unexpected biometric sign-out protocols frequently cause users to abandon their health portals entirely after a single frustrating session. Public health data indicates that nearly a third of patients aged sixty-five and older stop attempting to access their electronic health records independently within the first week of enrollment.
Without patient, human-centered guidance, the digital transformation risks leaving behind the very demographic that consumes healthcare services at the highest frequency.
Technology should bridge the distance between healing hands and vulnerable hearts, never erecting digital walls that shut patients out of their own care stories.
Bridging this widening divide demands structured administrative outreach techniques and thoughtful institutional interventions designed to meet patients at their current comfort level. Clinics dedicated to inclusive care have successfully implemented targeted strategies to boost asynchronous patient messaging compliance and portal adoption rates. The following structured overview highlights how specific demographic friction points align with preferred hardware and proactive clinical solutions.
| Demographic Segment | Reported Portal Friction Points | Device Preferences | Successful Onboarding Interventions |
|---|---|---|---|
| Elderly Patients (65+) | Tiny typography, complex multi-factor authentication, confusing medical terminology, and frequent session timeouts. | Desktop computers with large monitors and simplified tablet interfaces. | Dedicated in-clinic digital navigators, printed step-by-step visual guides with large fonts, and proxy-assisted family setups. |
| Low-Income Households | Unreliable internet connectivity, shared family devices, and lack of dedicated data plans for large application downloads. | Budget-friendly smartphones utilizing web-browser portals rather than native apps. | Community center tech kiosks, subsidized broadband partnerships, and SMS-based notification alternatives. |
| Limited English Proficiency | Language translation errors within lab summaries, culturally insensitive phrasing, and lack of multilingual technical support. | Mobile devices featuring automated screen-reader capabilities and translation extensions. | Bilingual digital health ambassadors, multilingual video tutorials, and culturally tailored user interfaces. |
Administrative teams play a pivotal role in transforming passive portal skeptics into active participants through persistent, empathetic communication and hands-on training. Implementing proactive outreach techniques ensures that digital tools serve as supportive companions rather than administrative barriers.
- Deploying specialized medical assistants to conduct brief, fifteen-minute digital orientation sessions during routine check-in procedures.
- Sending automated, friendly text message reminders with direct, secure login links that bypass multi-step password entries for low-risk viewing.
- Establishing dedicated telephone help desks staffed by patient representatives who can walk elderly users through laboratory result interpretations in real time.
- Providing physical laminated instruction cards at the front desk featuring large QR codes and simplified visual workflows for home reference.
Pharmacological interaction alerts frequently trigger notification fatigue among busy doctors managing multi-medication elderly cohorts.

Source: slideserve.com
Modern primary care ehr systems are transforming clinical workflows, empowering physicians to deliver compassionate patient care with remarkable efficiency. As clinics seek smarter financial pathways, evaluating the transparent canopyworks.com pricing model unlocks unprecedented opportunities for sustainable growth. Ultimately, embracing these innovative digital health solutions ensures that medical professionals can focus entirely on healing communities and brightening futures.
Inside the high-stakes environment of modern ambulatory clinics, digital prescription modules flash incessantly across computer screens, transforming healing spaces into arenas of constant digital interruption. When managing geriatric patients juggling ten or more daily prescriptions, physicians face a relentless barrage of amber and red pop-up windows warning of potential adverse drug reactions. This digital cacophony often obscures genuinely critical safety interventions behind a wall of repetitive, low-value notifications, eroding the very guardrails designed to protect vulnerable seniors.
The human cost of this relentless digital noise manifests as profound cognitive exhaustion among medical professionals striving to deliver meticulous care under severe time constraints. Every unnecessary alert demands an immediate mental context switch, draining the practitioner’s limited cognitive bandwidth during critical patient encounters. Addressing this systemic vulnerability requires a nuanced recalibration of electronic health record workflows to restore clinical intuition and protect patient safety.
Psychological Impact of Constant Clinical Decision Support Pop-Ups
The daily reality for primary care physicians involves navigating an unyielding tide of electronic warnings that fundamentally alter the psychological landscape of medical practice. Constant interruptions train the human brain to anticipate friction at every keystroke, fostering a pervasive sense of anxiety and defensive defensiveness during consultations. When clinical decision support tools cry wolf with minor, clinically insignificant drug-allergy alerts dozens of times a day, practitioners experience desensitization, a psychological defense mechanism where the mind tunes out the noise to survive the shift.
This systematic desensitization carries profound risks, as exhausted clinicians may begin blindly clicking through critical warnings just to regain control of their appointment schedule. The emotional toll builds silently, contributing to widespread burnout and moral injury among dedicated healers who feel trapped between regulatory demands and the imperative to maintain genuine human connection with their elderly patients. Transforming this adversarial software relationship into a collaborative partnership remains an urgent priority for modern healthcare administration.
Notification fatigue degrades clinical judgment, turning life-saving safety software into an administrative obstacle that physicians instinctively bypass under pressure.
Cognitive Recalculation During Redundant Drug Interaction Warnings
When a rushed practitioner faces a routine pop-up warning about a well-known, minor interaction between a common diuretic and a mild supplement for an octogenarian, an intricate mental calculation unfolds in milliseconds. The physician instantly evaluates the patient’s stable baseline, recalls previous successful months on the exact same regimen, and weighs the administrative burden of documenting an override against the zero statistical probability of an actual adverse event.
This micro-decision consumes precious mental energy, subtly degrading the clinician’s capacity for deep analytical reasoning later in the demanding workday.
To visualize this mental friction, picture an experienced geriatrician staring at a glowing monitor while an elderly patient speaks trustingly from an examination table chair. The physician’s eyes flicker rapidly between the patient’s expressive face and the neon-red software warning box, performing a silent internal calculus that pits years of clinical experience against rigid algorithmic mandates. In that fleeting second, the doctor must consciously suppress the mounting urge to dismiss the alert automatically, deliberately forcing themselves to re-verify dosage parameters just to ensure no subtle nuance has escaped their notice.
Customization Frameworks for Medication Safety Warning Systems
Implementing targeted software configurations can drastically reduce unnecessary interruptions while preserving robust safety nets for complex patient populations. Healthcare organizations must adopt structured customization strategies to filter out administrative noise and elevate genuinely actionable clinical intelligence.
- Establish tiered severity thresholds that completely suppress tier-three minor interaction warnings for stabilized chronic maintenance medications in patients over sixty-five.
- Configure specialty-specific user profiles that silence allergy alerts for inactive substances or mild sensitivities that do not involve systemic anaphylaxis risks.
- Implement intelligent batching protocols that aggregate non-urgent medication optimization suggestions into a single, reviewable end-of-visit summary rather than interrupting real-time prescribing.
- Design mandatory override documentation requirements to demand brief text justifications only for high-tier contraindications, while permitting single-click dismissals for routine informational prompts.
Specialized chronic wound documentation requires precise visual area mapping rather than generalized text-based progress notes.
Modern primary care electronic health records demand far more than standard text fields when managing complex clinical pathologies. Traditional narrative summaries frequently fail to capture the subtle, microscopic shifts occurring within compromised dermal layers during long-term patient recovery phases. By shifting toward advanced digital cartography and precise visual mapping methodologies, ambulatory care teams can securely capture objective metrics that transcend subjective human estimations, fundamentally transforming how chronic conditions are monitored over time.
Precision medicine relies heavily on reproducible data points, which makes spatial wound tracking an indispensable component of contemporary health informatics. When clinicians abandon vague descriptive notes in favor of rigorous coordinate-based geometries, treatment efficacy becomes quantifiable, verifiable, and entirely transparent across multi-disciplinary care teams.
Coordinate Based Tracking Mechanisms Used to Record Surface Area Reduction Over Consecutive Clinical Visits
Advanced ambulatory software implements sophisticated Cartesian grid overlays directly onto high-definition patient imagery captured during examination sessions. This coordinate system maps the exact X and Y axes of the epithelial defect, allowing software algorithms to calculate precise surface area reductions down to the square millimeter. Consecutive visits generate comparative overlays that instantly highlight stall points in tissue regeneration or accelerate intervention adjustments when regression is detected.
Transforming raw visual data into structured clinical insights requires standardized capture protocols that eliminate perspective distortion and lighting discrepancies. The following table Artikels the core methodologies, imaging benchmarks, and trajectory metrics utilized in advanced outpatient documentation suites.
| Measurement Methodologies | Photographic Documentation Standards | Healing Trajectory Indicators |
|---|---|---|
| Automated perimeter tracing via stylus-driven or touch-screen boundary mapping on digital tablets. | Standardized focal length, ring-flash illumination, and single-use calibration stickers placed adjacent to the wound margin. | Percentage of surface area reduction calculated weekly against baseline admission measurements. |
| Depth-sensing stereophotogrammetry utilizing multi-lens mobile sensors to generate volumetric topography. | Orthogonal camera positioning strictly perpendicular to the deepest bed of the lesion to prevent angular distortion. | Granulation tissue proliferation rates measured against standardized epithelial migration curves. |
| Thermal infrared imaging integration to detect localized inflammatory spikes and early occult infection zones. | Patient positioning logs ensuring identical anatomical orientation and ambient room temperature controls. | Exudate volume reduction correlates alongside diminishing periwound erythema surface boundaries. |
The visual environment of the modern examination room shifts dramatically as the clinician activates the high-resolution perimeter tracing tool on a sleek, wall-mounted clinical display. Under a cool, polarized ring-light, the practitioner gently guides a digital stylus along the jagged, hyperpigmented border of a recalcitrant venous leg ulcer. Each touchpoint registers on the screen with an audible, affirmative click, anchoring a luminous digital vector that encapsulates the irregular geometry of the lesion.
Beneath the surface layer, the software automatically cross-references the current perimeter against the previous month’s historical coordinates, instantly rendering a vivid heat map that glows in soft hues of amber and emerald. This chromatic shift reveals a twelve percent volumetric shrinkage in the deep tissue bed, validating the efficacy of the current enzymatic debridement protocol without relying on ambiguous estimations.
Objective visual mapping transforms subjective clinical observations into immutable chronological data points, securing verifiable accountability for every stage of outpatient tissue regeneration.
Tissue health classification demands absolute rigor, particularly when tracking complex pathologies like diabetic foot ulcers or stage-four pressure injuries within fast-paced outpatient workflows. Clinicians rely on standardized tissue composition percentages—quantifying viable pink granulation, pale fibrous slough, and necrotic black eschar—directly within the spatial mapping interface. This granular categorization prevents documentation fatigue while ensuring that reimbursement audits and specialty referrals are backed by indisputable, pixel-level evidence of patient recovery.
Rural medical clinics operate under severe broadband constraints that alter how patient databases synchronize with remote servers.

Source: tech-wonders.com
Deep within the rolling hills of isolated agricultural regions, community health centers face a silent daily battle against the digital divide, where fragile internet connections threaten the seamless flow of modern patient care. When wide-area network signals fade into static, dedicated physicians and nurses must rely on resilient local infrastructures to ensure that every critical health metric, allergy alert, and vaccination record remains instantly accessible inside dusty examination rooms.
Navigating these infrastructural bottlenecks requires a delicate balance of local data caching and intelligent background synchronization protocols designed to withstand intermittent connectivity. Clinics operating in remote terrains utilize encrypted edge-computing appliances—compact, rugged servers humming quietly beneath front desks—to capture electronic health records locally before attempting long-distance cloud handoffs. As the morning sun rises over valleys devoid of fiber-optic cables, these localized nodes empower medical teams to chart patient encounters with zero perceptible latency, transforming frustrating digital isolation into an opportunity for unbreakable clinical continuity and empowered community healing.
Local Caching Strategies During Connectivity Drops
Local caching mechanisms act as the invisible digital safety net for rural healthcare providers, capturing every keystroke, vital sign, and prescription order on local solid-state drives when wide-area networks unexpectedly collapse. Instead of freezing up or losing valuable clinical inputs, modern electronic health record platforms deployed in remote districts instantly shift write operations to secure, encrypted on-site memory buffers. These intelligent software layers queue pending database transactions locally, continuously monitoring broadband stability in the background while clinicians maintain their undivided attention on the patient seated across the desk.
Once a stable internet handshake is re-established with remote data centers, the caching engine orchestrates a silent, prioritized data upload that resolves conflicts automatically without disrupting ongoing consultations or compromising the chronological integrity of the patient file.
Analyzing offline data redundancy mechanisms for remote geographic practices reveals a fascinating intersection of modern distributed systems engineering and everyday clinical survival. When broadband towers go dark due to severe weather or geographic isolation, rural clinics cannot simply pause operations until engineers restore connectivity miles away. To prevent catastrophic data loss, these facilities implement multi-tier redundancy architectures, mirroring primary patient databases onto localized network-attached storage units located right down the hall from the dispensary.
These secondary nodes employ continuous incremental snapshotting, capturing every minor modification made to chronic disease management plans or acute trauma charts every few minutes. Furthermore, cryptographic hashing ensures that when synchronization eventually resumes, the remote cloud servers can mathematically verify that no local records were altered, duplicated, or corrupted during the offline period. This rigorous approach transforms vulnerable rural outposts into fortresses of data integrity, proving that advanced fault tolerance is just as vital to a country doctor as a reliable stethoscope or a well-stocked medicine cabinet.
Emergency Synchronization Procedures Following Wide Area Network Outages
Restoring digital harmony after a regional network failure demands a disciplined, step-by-step operational choreography to prevent data collision and ensure the safe merging of offline and online patient records. Frontline administrative staff and IT coordinators must execute standardized recovery sequences that prioritize urgent clinical updates over routine administrative data packets.
- Initiate automated diagnostic ping sequences to verify the sustained physical and cryptographic stability of the wide-area network connection before manually triggering any bulk data transfers.
- Execute a read-only lockdown on local edge caches to freeze patient record modifications, preventing race conditions while the central server reconciliation script parses the chronological transaction logs.
- Review the automated exception queue generated by the electronic health record reconciliation engine, manually resolving any conflicting timestamp entries for patients who were treated across multiple offline terminals.
- Broadcast a confirmation clearance status across internal clinic messaging channels once the remote cloud server verifies that 100 percent of queued local transactions have been successfully synchronized and indexed.
Hardware Resilience Specifications For Severe Weather Events
Protecting clinical data infrastructure against punishing meteorological conditions requires investing in specialized hardware engineered to endure extreme voltage fluctuations, high humidity, and prolonged electrical grid failures common in remote regions. Clinics situated in hurricane-prone coastlines or blizzard-swept mountain passes deploy industrial-grade server enclosures equipped with robust thermal management systems and double-conversion online uninterruptible power supplies. These heavy-duty power units instantly bridge the gap during sudden grid collapses, providing clean, conditioned electricity that shields sensitive database components from damaging power surges.
Additionally, solid-state storage arrays featuring military-grade shock resistance ensure that physical vibrations from howling winds or nearby lightning strikes do not fracture delicate magnetic read-write heads, keeping local patient archives safe, secure, and fully operational when the community needs healing the most.
Resilience in rural healthcare is not merely about surviving the storm; it is about maintaining an unbroken chain of trust between the healer and the healed, regardless of how fragile the digital tether may be.
Last Recap
Ultimately, the true measure of any digital health platform lies in its quiet ability to elevate human empathy over administrative burden, restoring the sacred focus back to the healing relationship between doctor and patient. By thoughtfully bridging the gaps between software design, clinical workflow, and technological reliability, we pave the way for a more intuitive, compassionate, and resilient future in medicine.
